For most of the last decade, “digital health” was the umbrella term venture investors used to talk about anything touching a hospital, a patient, or an insurer. Over the last five years, that umbrella has narrowed and sharpened into something more specific: artificial intelligence built natively for healthcare, designed from day one to read a chart, read a scan, write a note, or design a molecule.
The macro picture: a crash, a trough, and an AI-fueled rebound
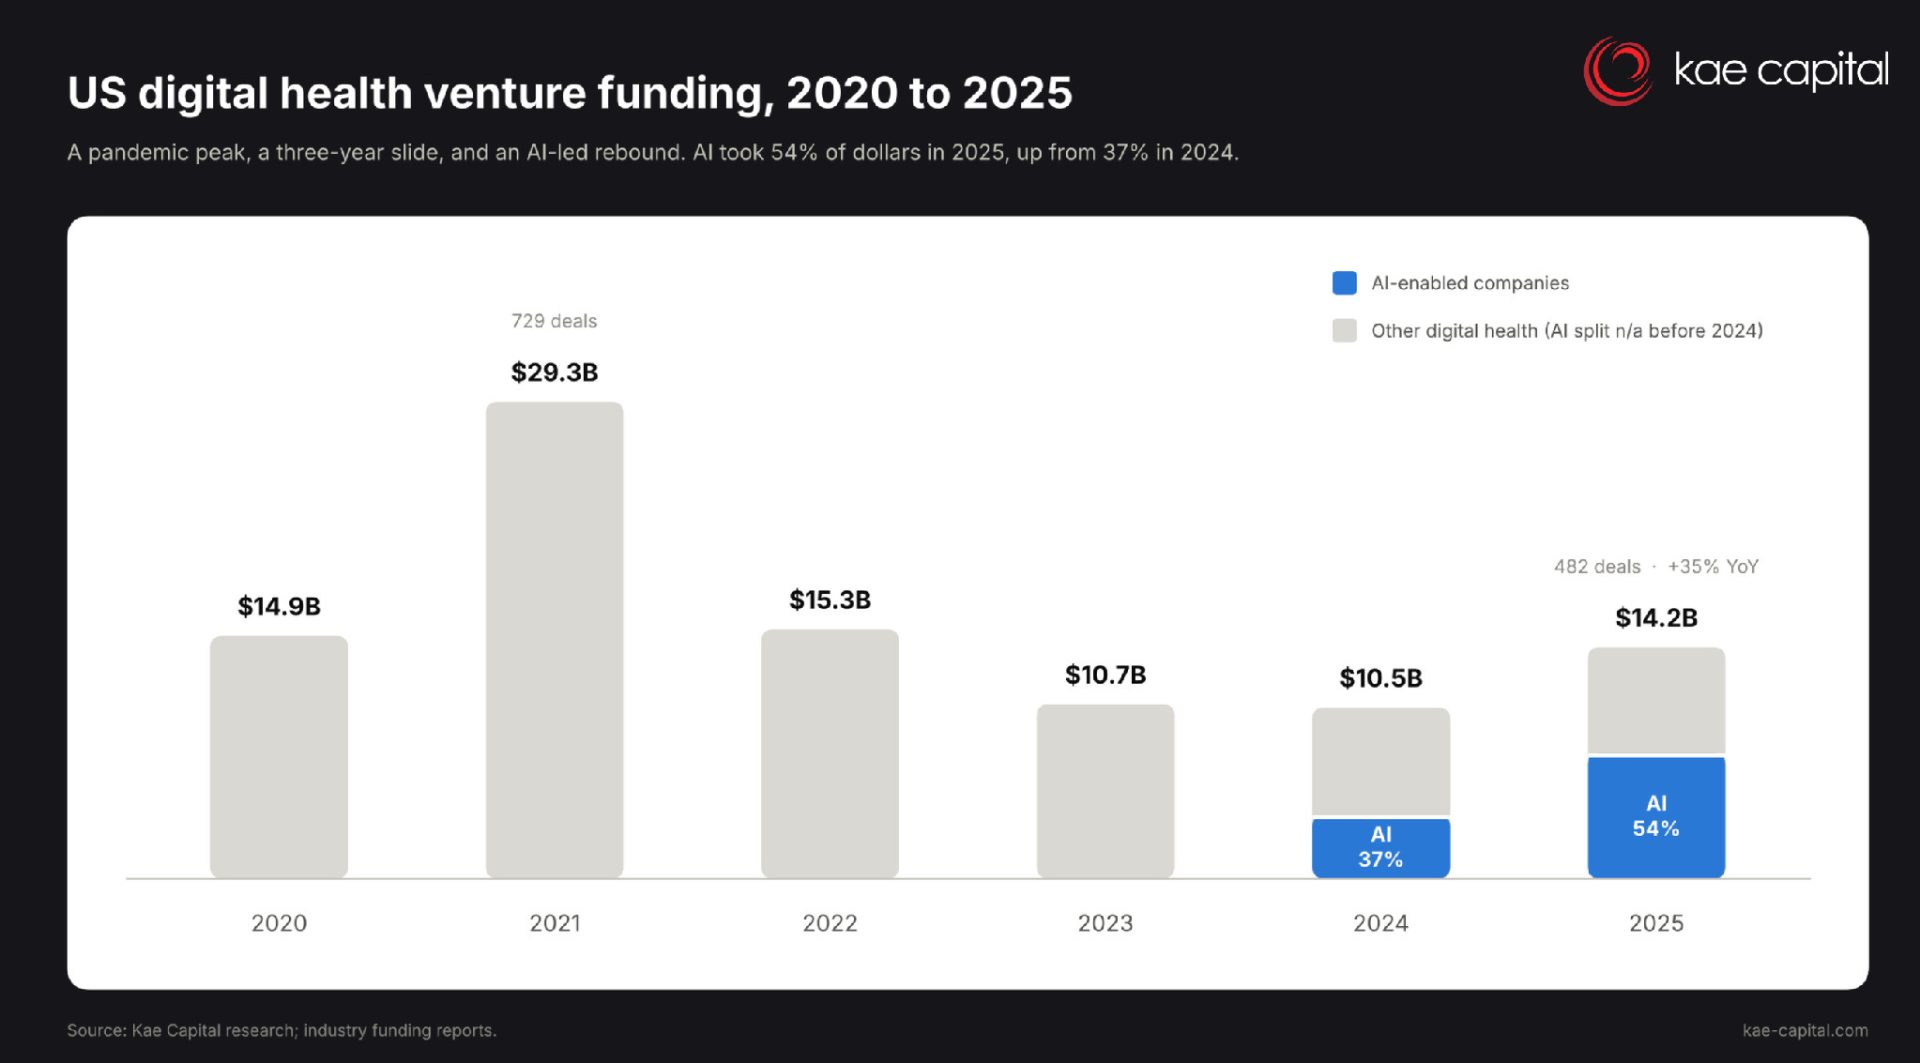
Digital health venture funding peaked at roughly $29.3 billion across 729 deals in 2021, more than double the prior record set in 2020 ($14.9B), as pandemic-era enthusiasm and near-zero rates pulled forward years of capital deployment. What followed was a hard correction: $15.3 billion in 2022, then $10.7 billion in 2023, the lowest total since 2019, and a further dip to roughly $10.5 billion in 2024.
2025 broke that slide, but not evenly. Total digital health funding rose to $14.2 billion across 482 deals, a 35% jump from 2024, and virtually all of that growth was AI. AI-enabled companies captured 54% of all digital health dollars in 2025 (about $7.7 billion), up from 37% the year before, and commanded roughly a 19% premium on deal size relative to non-AI peers, rising to a 61% premium at Series C. Twenty-six mega-rounds of $100 million or more accounted for 42% of the year’s total funding, the highest concentration since the 2021 bubble, and the market minted 15 new unicorns compared with just six in 2024. In short: the broader digital health market is still well below its pandemic peak, but healthcare AI specifically is now the thing keeping the category alive, with a small number of very large rounds doing most of the work.
The prize is enormous (US healthcare runs at roughly 16 to 18% of GDP), and it is worth being clear-eyed about how it behaves. “The profit pool sits in three or four specialties. Cancer, cardio, your top Cs. In cancer, roughly 70% of the payout flows through drugs.” That framing (follow the reimbursement, not the clinical narrative) runs through nearly every category below.

AI-native drug discovery and biotech: the biggest checks in the market
The single largest checks in US healthcare AI over the last five years have gone to companies trying to compress the drug discovery timeline using generative models, protein-design AI, and large-scale lab automation. This is also the subsector where the newest entrants have raised the fastest: Xaira Therapeutics launched in April 2024 with $1 billion already in the bank, before it had a single drug in the clinic, and Chai Discovery, founded in 2023, closed a $400 million Series C in July 2026 at a $3.8 billion valuation, roughly tripling its valuation from seven months earlier.
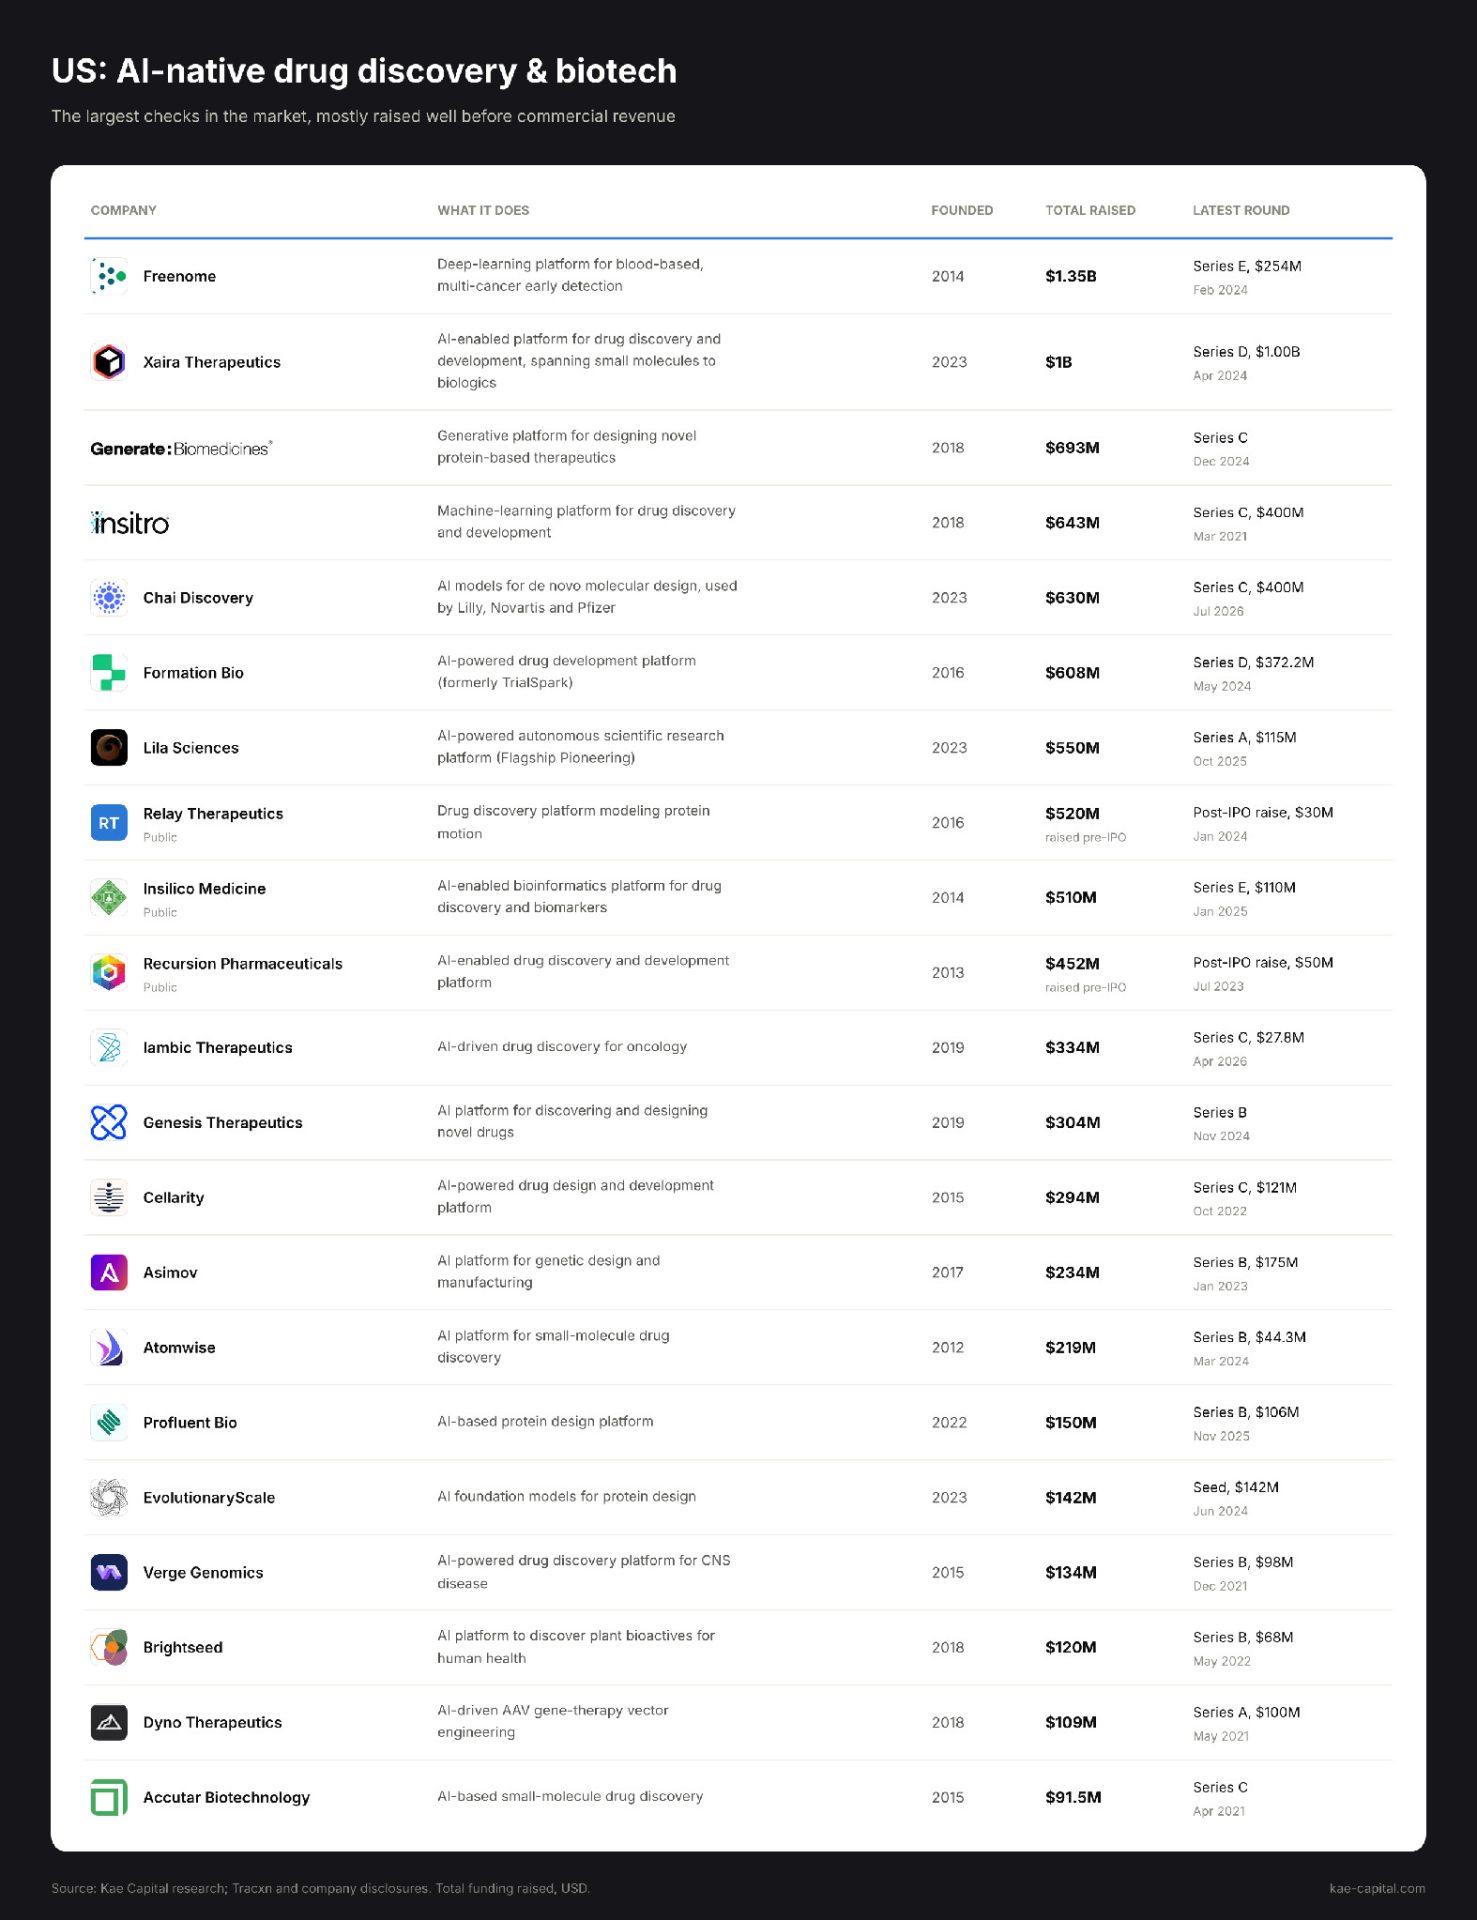
Two things stand out. First, the sheer size of first checks: Xaira and Chai Discovery both launched or scaled with nine-figure-plus rounds before commercial revenue existed, a pattern almost unheard of outside frontier AI labs. Second, the public comps (Recursion, Relay, Insilico Medicine) show that even after years of funding and a public listing, revenue in AI-native drug discovery remains modest relative to valuation. The bet is still almost entirely on future pipeline value, not current commercial traction.
There is a structural reason for that, and it applies well beyond the biggest name. “In R&D there is almost no way to measure ROI. It will take forever to actually deliver on it. For you to scale, your product has to be transformational, and the sales processes get longer and longer.” Reference-selling, the engine of enterprise software growth, barely works here either: “On the R&D side, pharma is completely closed. No one wants to talk about what they’re doing. It’s considered a trade secret, so the chance you get a reference out of anyone goes to zero.” That is why the drug-discovery names raise the most and disclose the least: the capital is a substitute for the commercial proof points that other categories can generate in months.
AI diagnostics and imaging: where revenue is starting to catch up
Unlike drug discovery, the diagnostics and imaging AI companies are further along commercially. Most have FDA clearances, hospital contracts, and real, if still early, revenue.
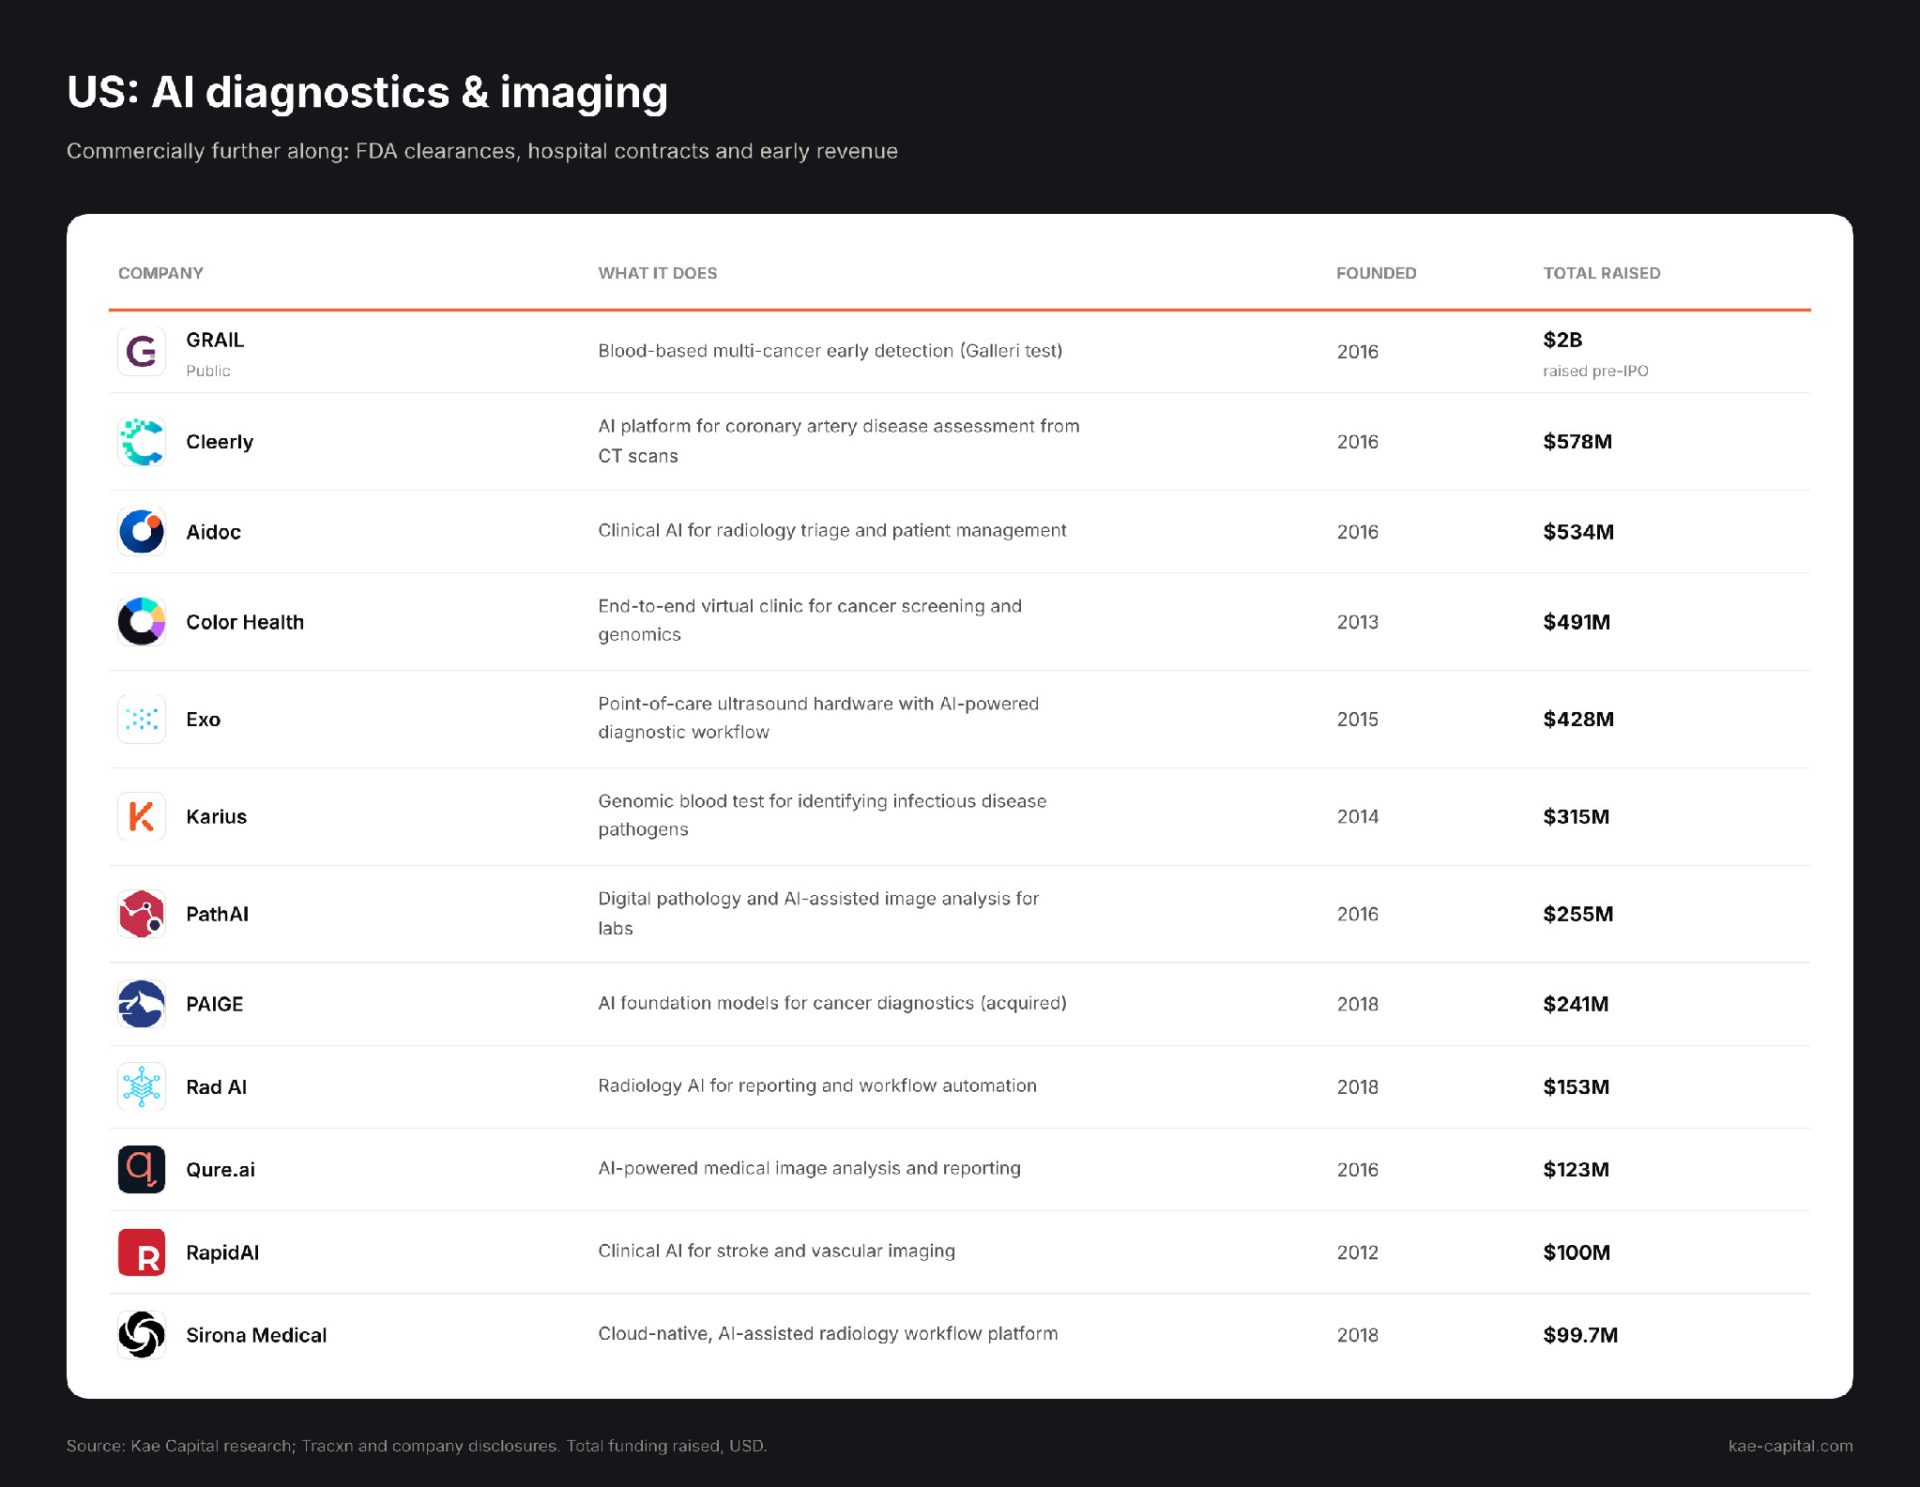
This subsector has also seen the market’s clearest exit signal: Paige.AI was acquired rather than continuing to raise, and GRAIL, after being spun out of Illumina and going public, remains the highest cumulative fundraise on this list at just over $2 billion, reflecting how capital-intensive it is to commercialize a genomic screening test at scale.
Radiology AI was the first place AI demonstrably worked in healthcare, and that is exactly the problem: it has since become the most commoditized. “There are so many products now that a radiologist has ten different ones and can say, for this image I want to use product one, or product three, and compare the results. Every imaging platform has an app store of these applications, pay-as-you-use.”
“If you’re just an algorithm and don’t have anything else around it, the chances of you getting commoditized over time are very, very high. You might still be the preferred solution, but people will negotiate harder and harder with you and your monetization keeps going down rather than up. Then you’re on a hamster wheel.” The implication for investors is that a diagnostic algorithm is only durable when it is wrapped in workflow the customer can’t easily swap out, and that the single most important gating item for any new entrant is FDA clearance.
Ambient clinical documentation and AI copilots: the fastest-growing corner of the market
If one product category defines “healthcare AI” for a doctor in 2026, it’s the ambient scribe: an AI that listens to a patient visit and writes the clinical note. This category didn’t meaningfully exist five years ago and is now home to some of the largest and fastest-moving rounds in the entire healthcare AI market.
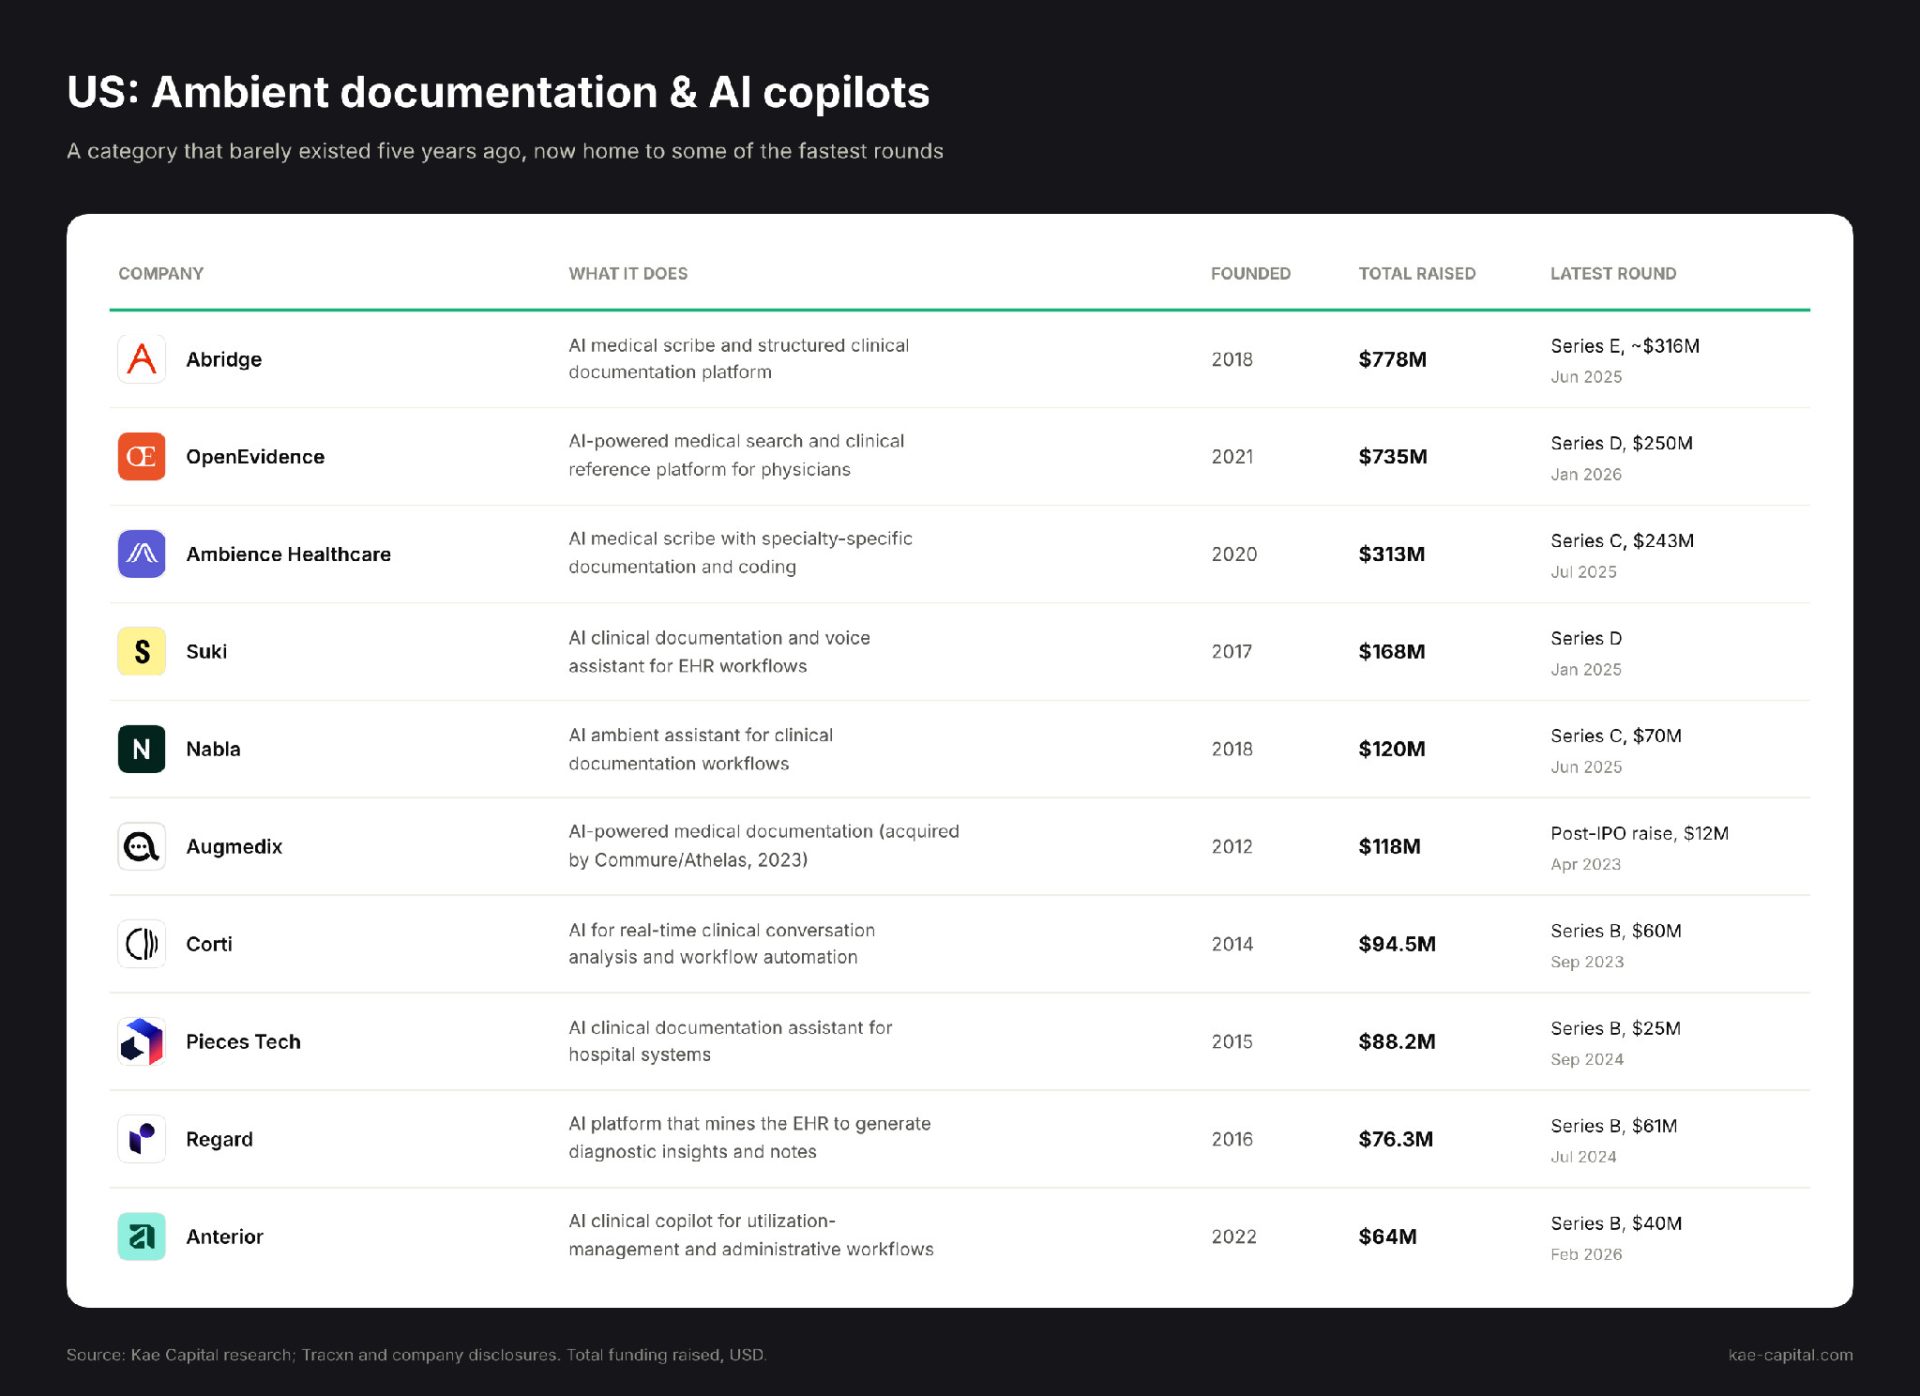
Abridge’s trajectory is the clearest illustration of how fast this category is moving: it went from a ~$300 million Series E at a $5.3 billion valuation in June 2025 to closing an extension of the same round two months later, doubling its valuation in roughly four months. OpenEvidence followed a similar arc, doubling its valuation to $12 billion with its January 2026 round barely a year after breaking into the top tier of the market. Andreessen Horowitz, General Catalyst and Kleiner Perkins each participated in at least five of 2025’s healthcare AI mega-deals, and this category (ambient documentation and clinical copilots) was where most of that overlap happened. Kae itself has a position in this category through Supa Health, an AI scribe and RCM platform focused on behavioral health clinics, and our own experience there matches what we hear across the market: scribe revenue comes quickly, because adoption is fast and the value is obvious to the clinician, while converting the same customer onto the RCM product is a slower, harder sell.
Healthcare data, analytics and interoperability platforms
A second cluster of capital has gone into companies that don’t sit directly in the clinical workflow but instead aggregate, structure, and monetize the underlying healthcare data those AI products need to work: real-world data platforms, EHR-adjacent data layers, and life-sciences commercial analytics.

This group tends to raise less frequently but in larger increments, and two of them, Truveta (backed directly by health systems like Providence, Regeneron and Northwell as investors) and Commure (now valued at $7 billion and reportedly weighing a public listing), sit closest to becoming the next wave of healthcare AI IPOs.
Administrative automation, revenue cycle and patient-access AI
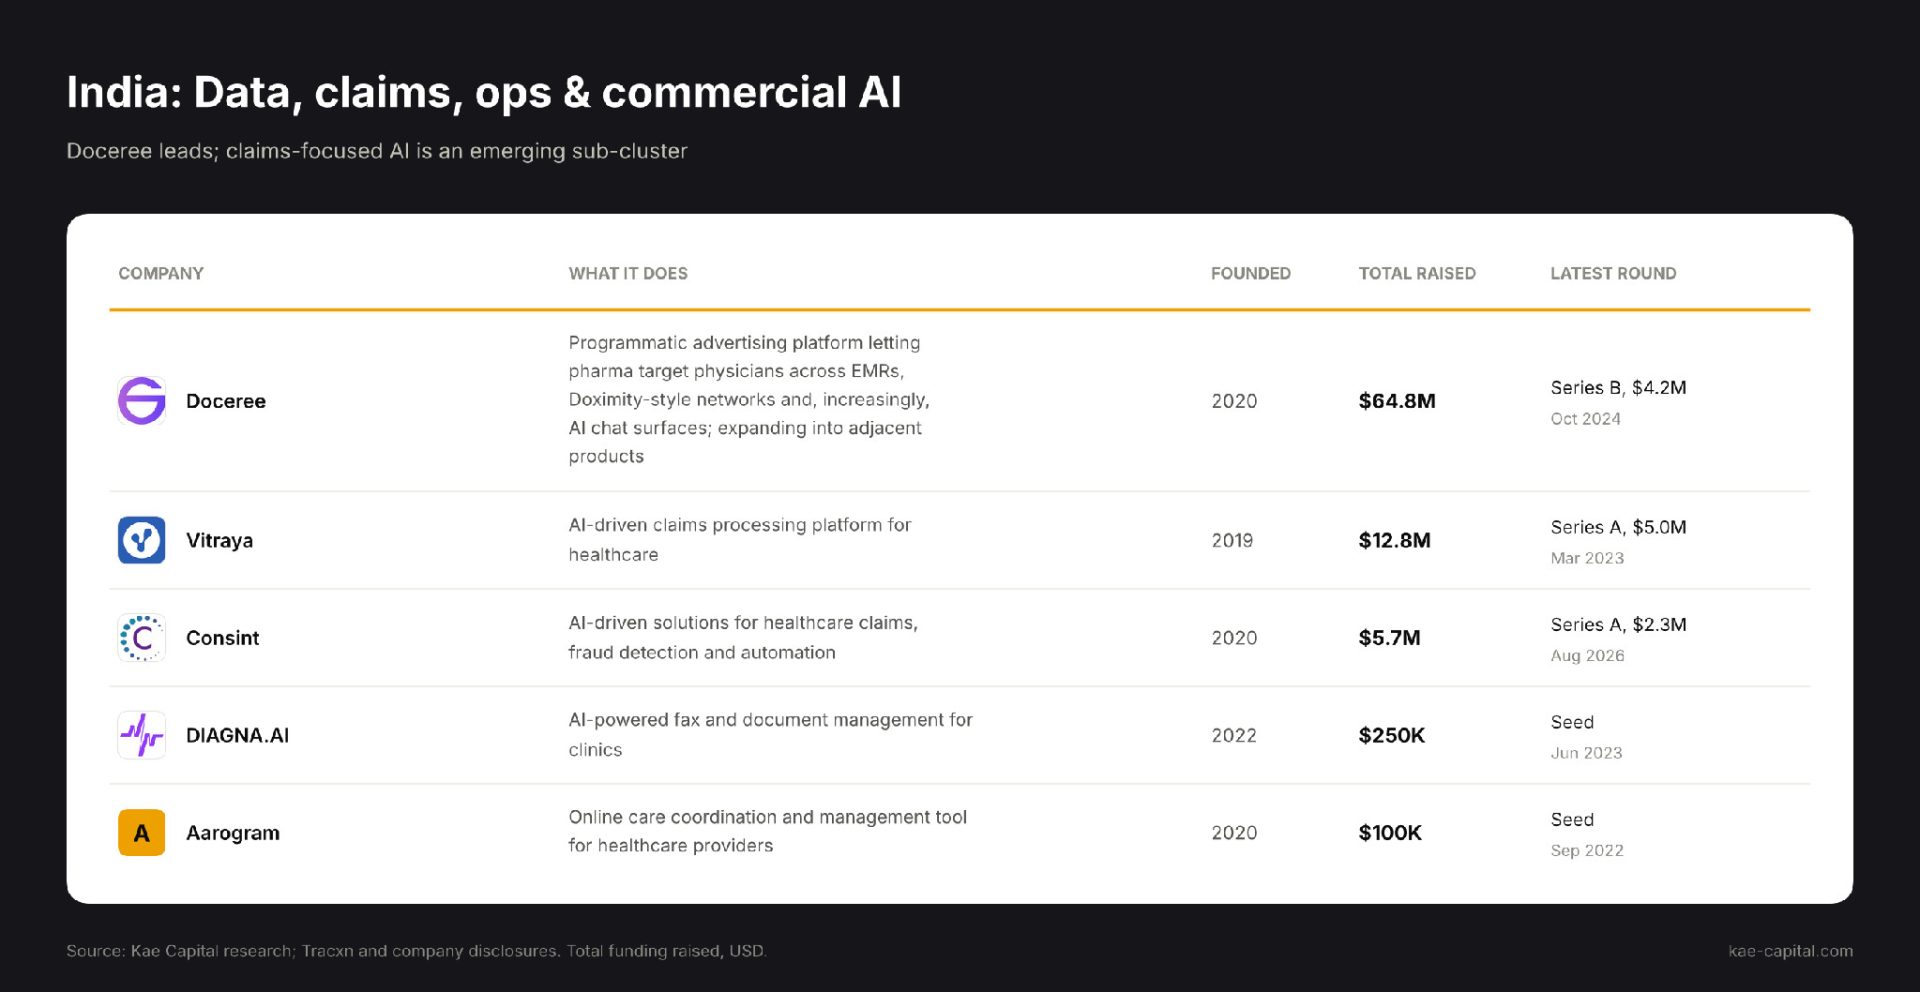
The most crowded part of the market by deal count is administrative AI: companies automating prior authorization, medical coding, patient scheduling, claims and reimbursement, and the phone calls and paperwork that consume a large share of every health system’s back office. Revenue cycle management (RCM) and medical coding specifically are themselves a dense sub-niche within this category, with a cluster of well-funded, pure-play claims/coding companies alongside the broader patient-engagement and voice-agent players. Given how fast this space is moving, we have almost certainly missed a few companies here.
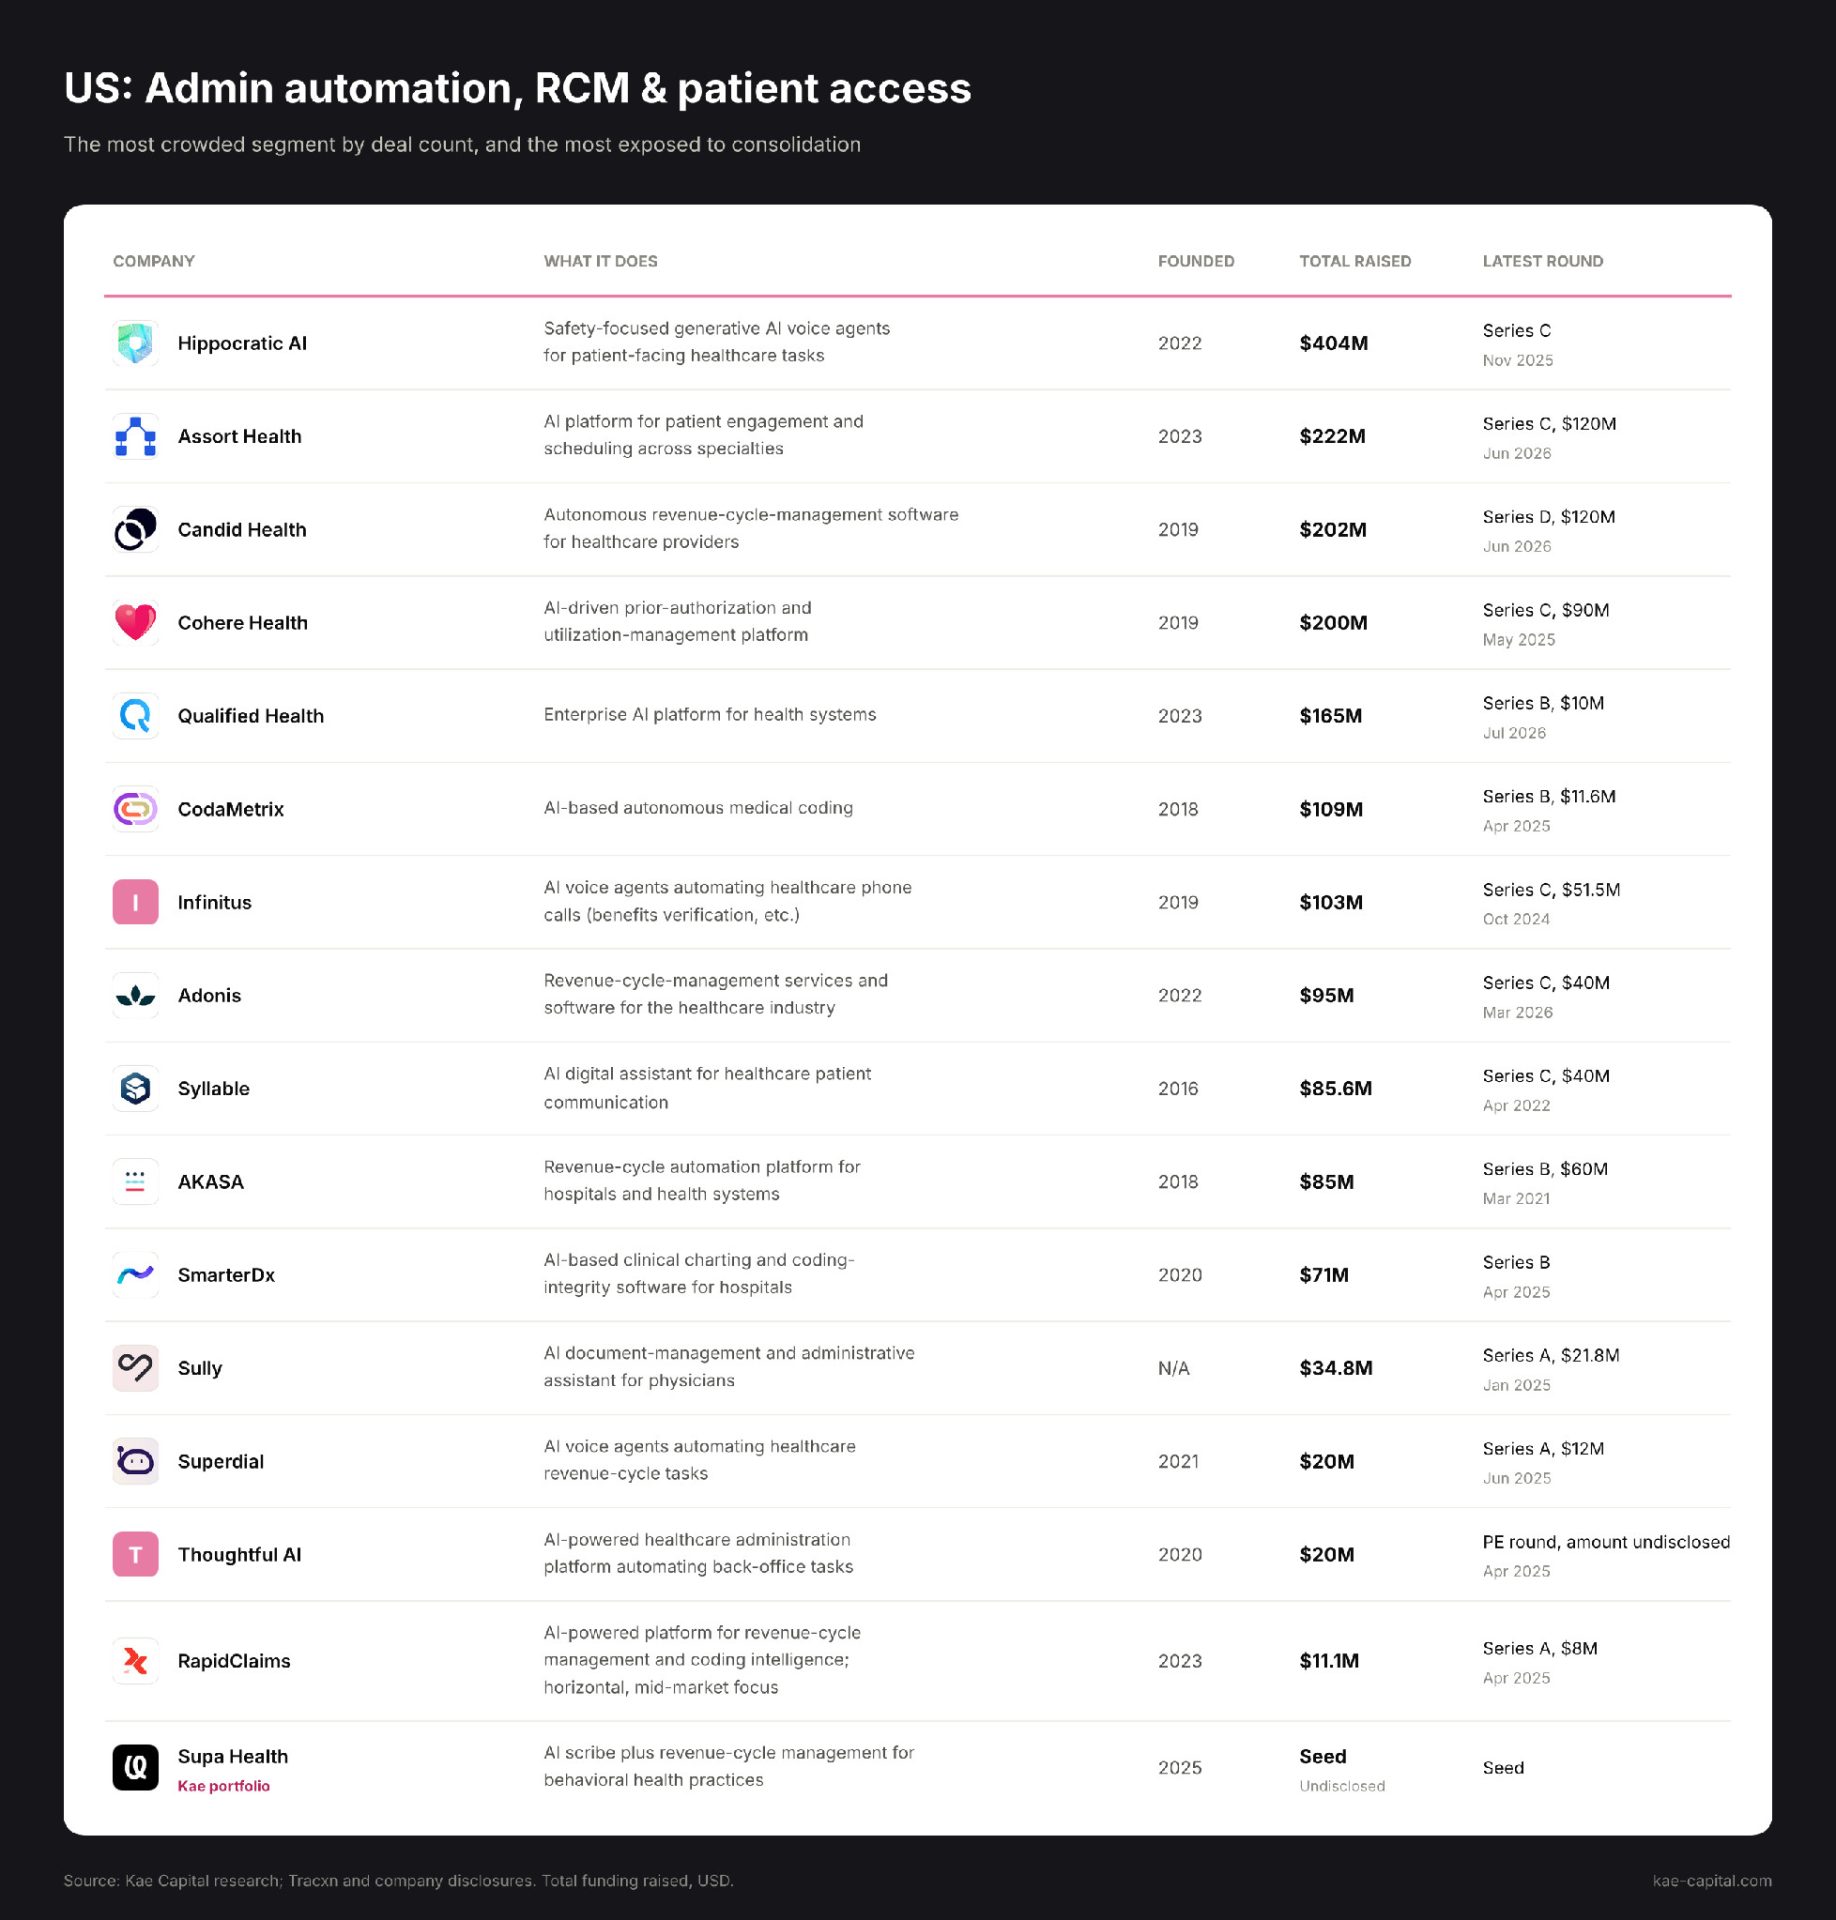
This is also the segment most exposed to consolidation risk: Olive AI, once one of the best-funded companies in this category, wound down its core business and sold off its assets after raising hundreds of millions, a reminder that “AI will fix healthcare’s paperwork problem” has been an expensive thesis to underwrite, and not every well-capitalized entrant survives. The RCM/claims niche specifically has already produced a different kind of consolidation signal: Machinify, an AI payment-integrity platform that had raised comparatively little ($10M since 2015), was acquired by private-equity firm New Mountain Capital in January 2025: a roll-up exit rather than a venture-scale outcome, and a reminder that not every claims-AI company needs (or gets) a venture-style trajectory to have value. AKASA, the oldest pure-play RCM automation company on this list, is also the one with the clearest disclosed traction: an estimated ~$82 million run rate against $85 million raised, a far tighter capital-efficiency ratio than most of its more richly funded, more recently founded peers like Candid Health and Adonis.
For the last twenty years people have just done body-shopping: whole floors of people in India and the Philippines, very high turnover, hiring 18-to-25-year-olds who don’t really carry the knowledge they need.
A Founder of an AI RCM company we spoke with puts it, “Tech is not new to the space either. I’ve seen people use UiPath and Automation Anywhere-type products, and they don’t work. And even the best of the best with billions of dollars, the big EHR companies, have been trying to automate RCM for years and been unsuccessful.”
The reason is that revenue cycle is not one workflow but thousands. “Every specialty, every system, every workflow is different. I have two behavioral health clients, and client one and client two are completely different in how they operate. You can’t say, I’m going to build a SaaS product and sell it to a thousand practices. That doesn’t work in this model.” Worse, the operating knowledge isn’t written down anywhere: “Most of the knowledge of how a practice processes its RCM sits in the heads of users. It’s not documented. You can’t say, I’m going to replace your people with AI agents tomorrow at the flip of a button, because there is no knowledge base to train on. You have to build it from the beginning.” That is why so many entrants are narrow (coding-only, or a single specialty), and why the space is so crowded at the point-solution level. “Pick any area, coding for example: there are at least 100 players doing coding automation. From one model to the next it may be a 5% variance. The key is distribution.“
There is an equally consistent view on how to sell it, and it cuts against the instinct of most AI founders. “The way to pitch RCM is to say: we will do your revenue cycle, end to end, and this is the rate”. “Whether it is automated or services, beyond a point the customer doesn’t care. The customer wants an end-to-end solution more than anything else. If you say, I will just automate, then the customer has to figure out what your automation rate is and how they handle the remaining charts. That makes the sale much harder. It’s not that you can’t sell it that way. It just makes it much harder.” It also dissolves the stickiness objection that usually protects incumbents: “If you are 50% cheaper than the current vendor, why will they not shift?” AI, in other words, changes RCM economics not by selling automation to a billing office but by letting a new entrant underprice a services contract, which is exactly why the category’s exits (Machinify) and its most strategic new money are increasingly coming from investors who already own traditional RCM services businesses and want to automate their own cost base. And it explains the moat that does exist. “Healthcare is a lazy industry,” is something that resonated amongst all the operators we spoke to. “You adopt technology slowly, but you also don’t switch often. Point solutions you can swap out. Switching a coding vendor is a couple of months. But if you’ve built something completely customized that works in their setting, it is impossible for them to unplug it, because the only way to unplug is to hire the people back and go back to working the way they did five years ago.”
Adjacent categories worth watching
A handful of companies don’t fit neatly into the buckets above but are shaping specific corners of the market: Eleos Health ($126.0M raised, Series C in January 2025) applies AI to behavioral-health documentation and outcomes tracking; SafelyYou ($102.5M raised, Series C in January 2025) uses computer vision for fall detection and safety monitoring in senior care facilities; and Pearl ($91.3M raised) brings AI-based diagnostic support to dental practices, an often-overlooked specialty vertical.
The larger omission from the five categories above is the payer side. Almost every company in this piece sells to providers or pharma; comparatively few sell AI to the insurers who actually pay the claims, even though payers carry as heavy a transactional load as the hospitals they reimburse. Two India-rooted, US-selling companies are worth knowing here. HiLabs (founded 2014; $41.0M raised, Series B of $39M in March 2024; ~$128M Tracxn-estimated revenue for CY2025, a figure we’d treat with particular caution) does real-time validation of the provider data payers ingest (names, locations, services, accepted plans), where a regulatory requirement to publish accurate directories creates the demand, and has since expanded into clinical-data accuracy and value-based-care compliance products. Autonomize AI (founded 2021; $32.0M raised, Series A of $28M in May 2025) sells AI agents into adjacent payer workflows. Payers are hard customers because they do not refer. “If you sell to a health system, the buying manager will act as your reference to another health system. By the time you reach payers, that tendency reduces. It’s a concentrated, competitive field and no one wants to disclose what they’re doing.” The category is smaller and slower to build in, but it is also far less crowded than provider-side RCM.
What the pattern says about where this market is headed
Five years of data point to a market that has bifurcated rather than simply grown. Broad digital health funding is still roughly a third below its 2021 peak, but healthcare AI is where nearly all the growth, and nearly all the largest checks, are concentrated: 2025’s 26 mega-rounds of $100M+ drove 42% of total digital health dollars, and 15 companies crossed into unicorn territory in a single year. The subsectors with the most capital velocity (ambient documentation, AI drug discovery, and diagnostics) are also the ones where round sizes and valuations are compounding fastest: Abridge doubling its valuation in four months and OpenEvidence doubling to $12 billion within about a year are not isolated events, they’re the pattern.
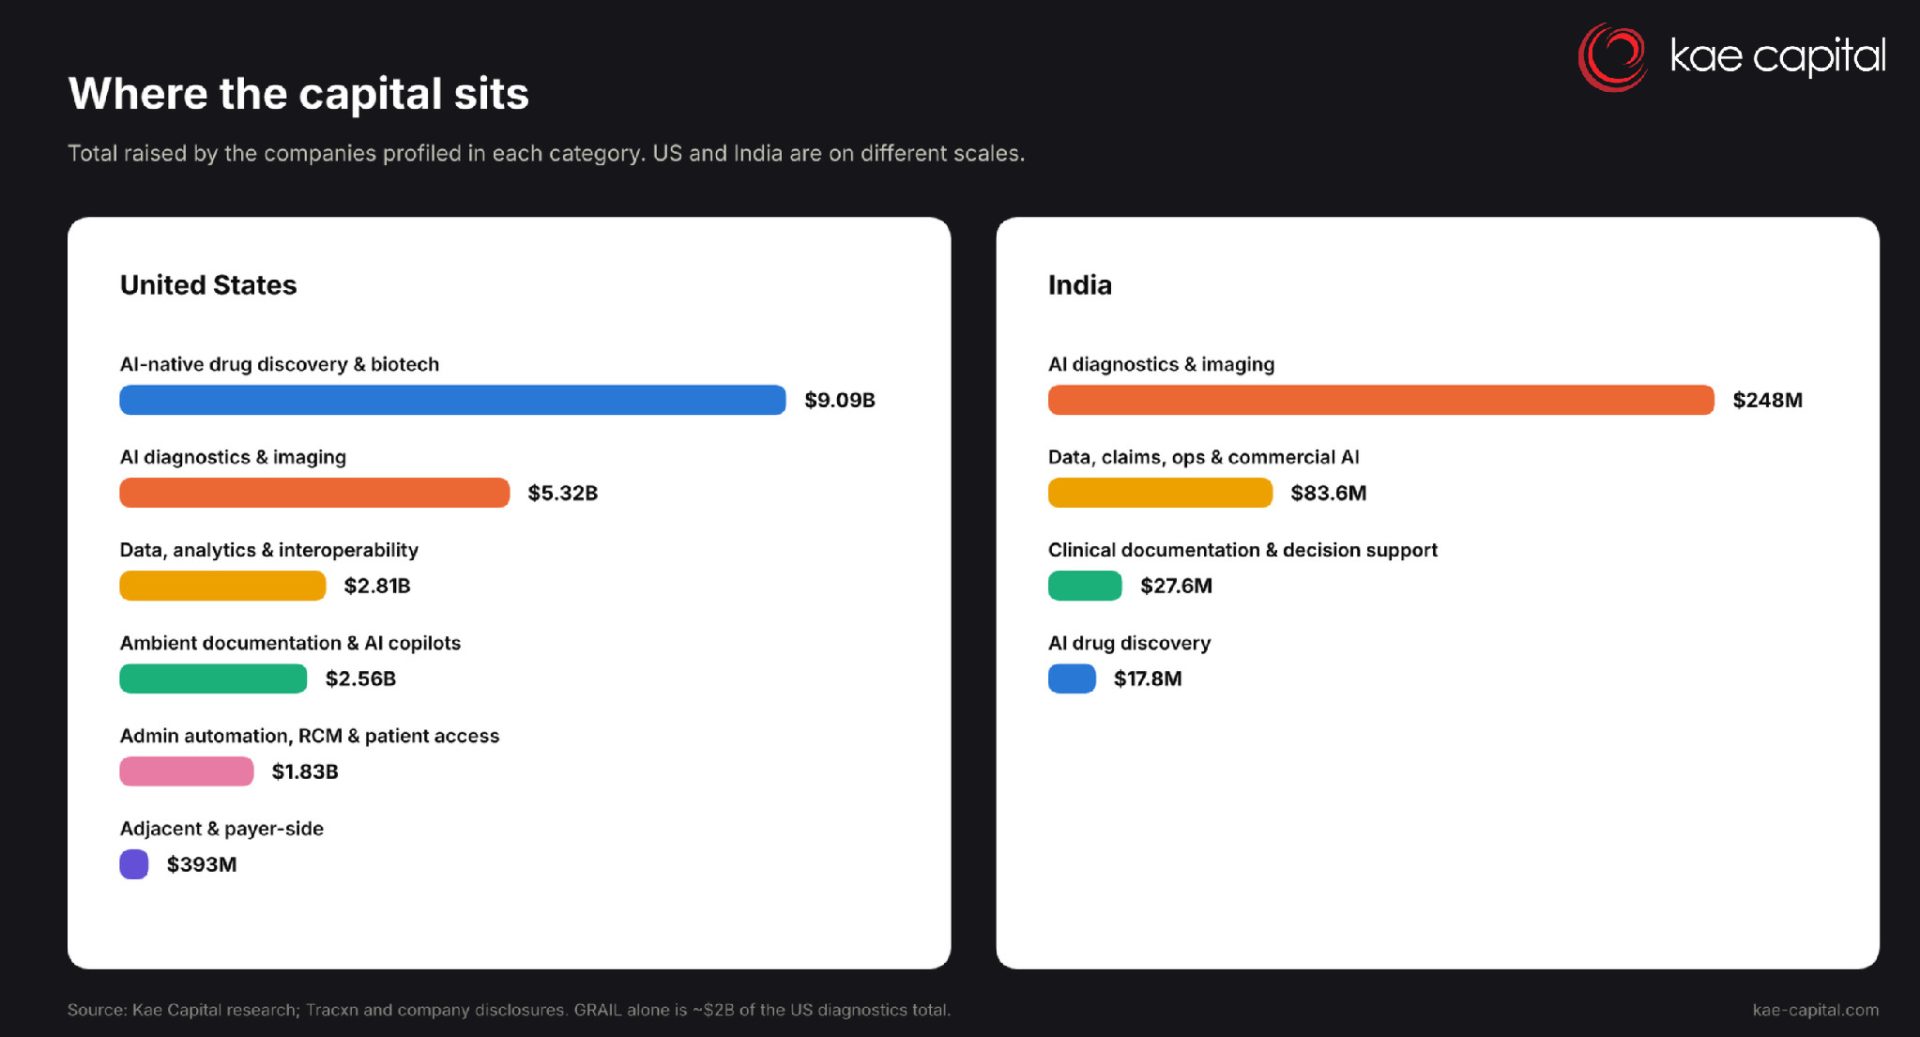
At the same time, revenue durability remains the open question across almost every category. Even the best-capitalized AI-native biotechs (Xaira, Chai Discovery, Generate Biomedicines) are still pre-revenue or near it years after founding, and even the more commercially mature diagnostics and documentation companies mostly sit in the $15M–$100M estimated run-rate range despite raising hundreds of millions and, in several cases, being valued in the billions. The companies converting funding into durable, disclosed revenue at scale, namely Tempus ($1.27B in 2025 revenue, with Q4 revenue up 83% year-over-year, now public), Axtria ($821M estimated), and Komodo Health ($187M estimated), tend to be the ones that have been operating for a decade or more, not the newest entrants. For investors, that gap between funding velocity and revenue maturity is probably the single most important thing to underwrite in this market over the next few years.
A useful framework founders can use to study the market is to picture a 3×3 grid: the customer on one axis (provider, payer, pharma) and the job on the other (grow revenue, cut cost, or accelerate R&D). Each of the nine cells has a different difficulty of sale. Selling revenue growth is easiest anywhere: “If you show a 2x ROI, your product will sell, because within three or four months you can see a very measurable impact.” Cost optimization is harder: “the ROI becomes difficult even to calculate; cost is affected by twenty other factors, and a particular cost line is always a small percentage of revenue, so the expectation moves to 4x”, and R&D is hardest of all. Lay our categories onto that grid and the pattern in the data resolves. RCM and administrative AI sell cost reduction to providers, which is why the winning pitch is end-to-end outcome pricing rather than “we automate X%.” And AI drug discovery sits in the pharma-R&D corner, where ROI is nearly unmeasurable and references are unavailable, which is why it has raised the most money and disclosed the least revenue. The bifurcation in the funding data isn’t random; it tracks how provable each category’s value is.
India healthcare AI market map
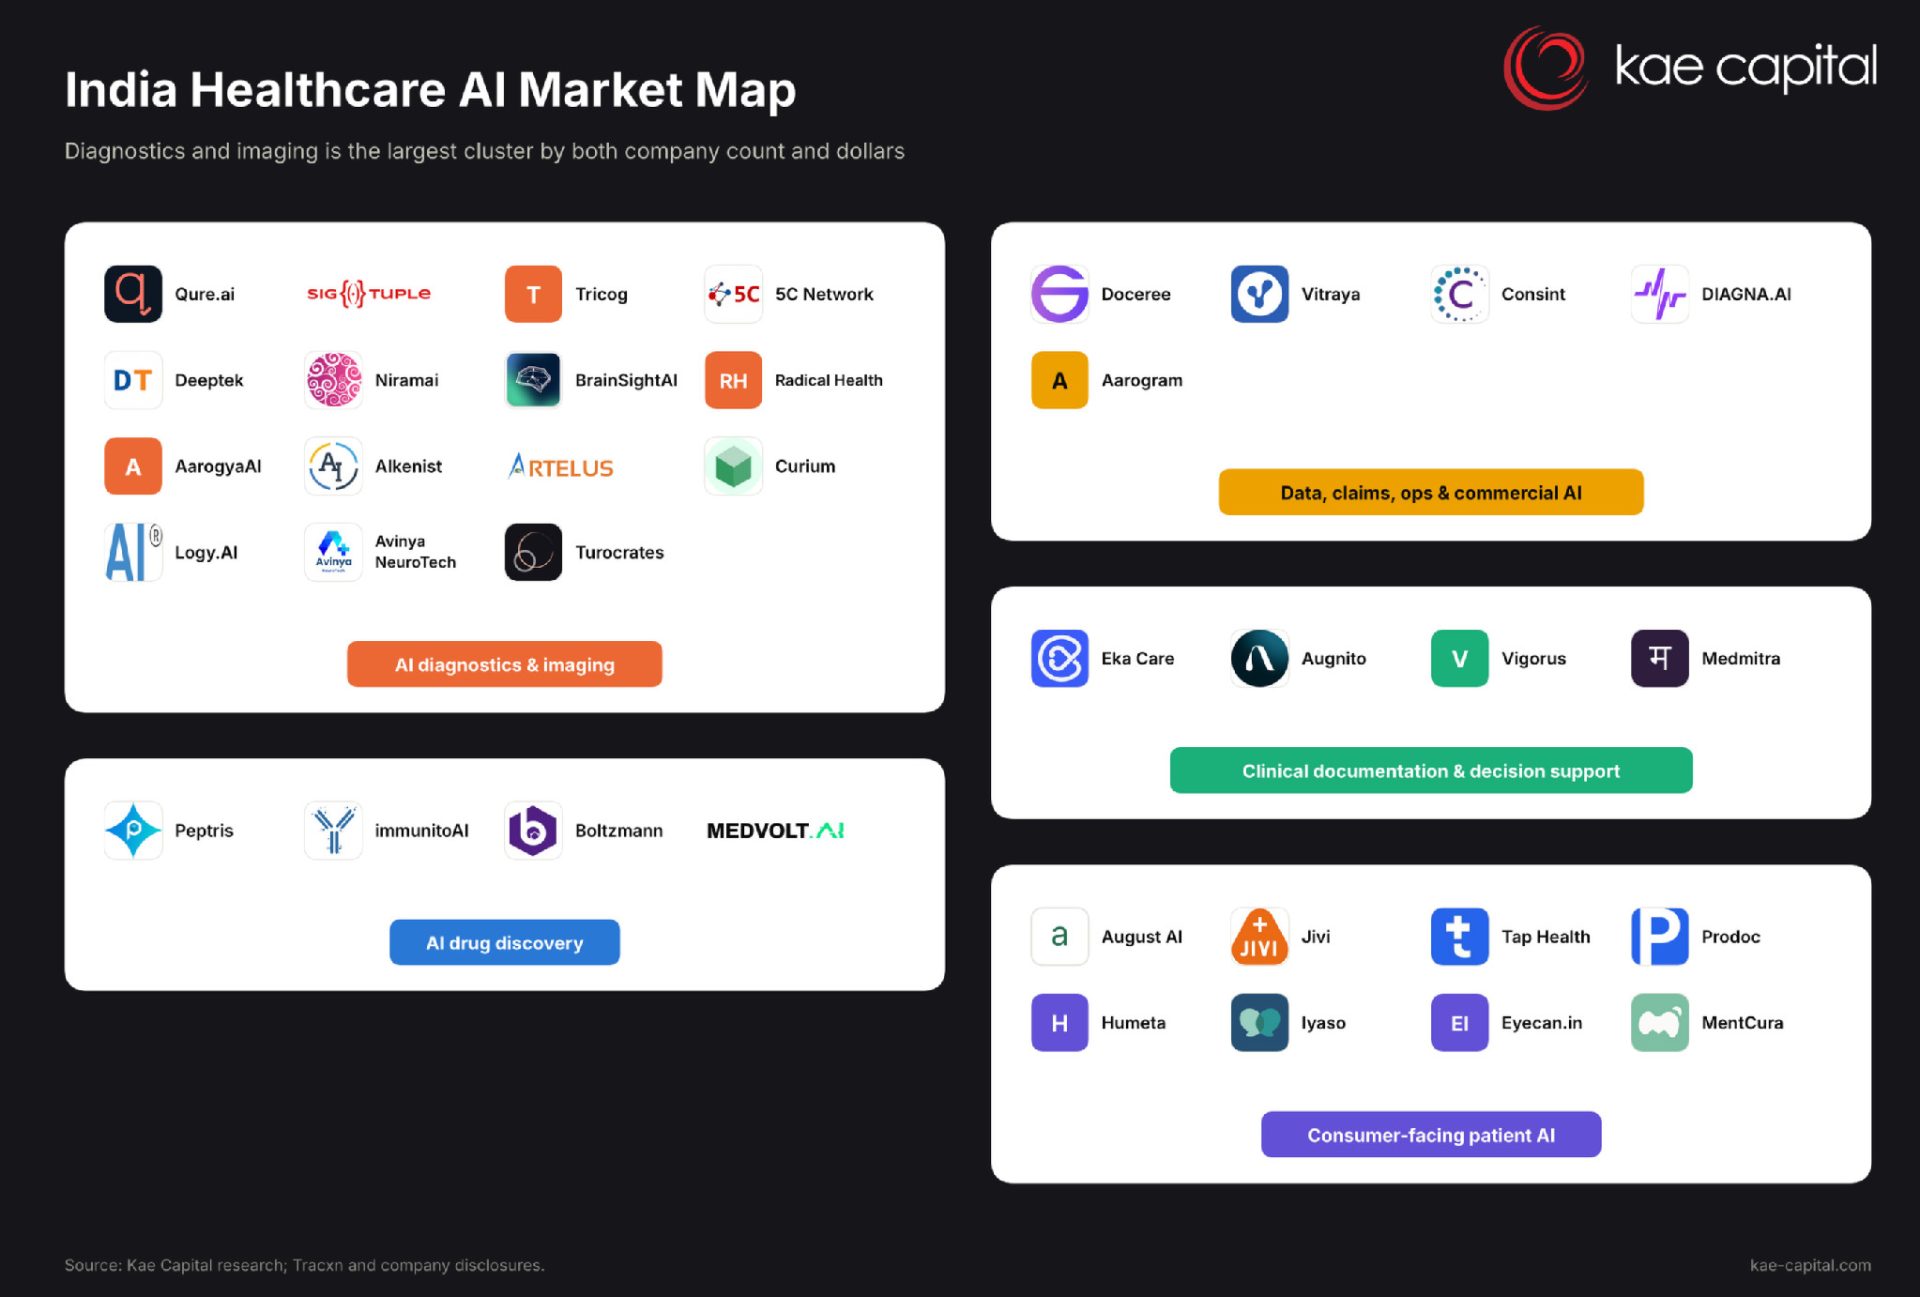
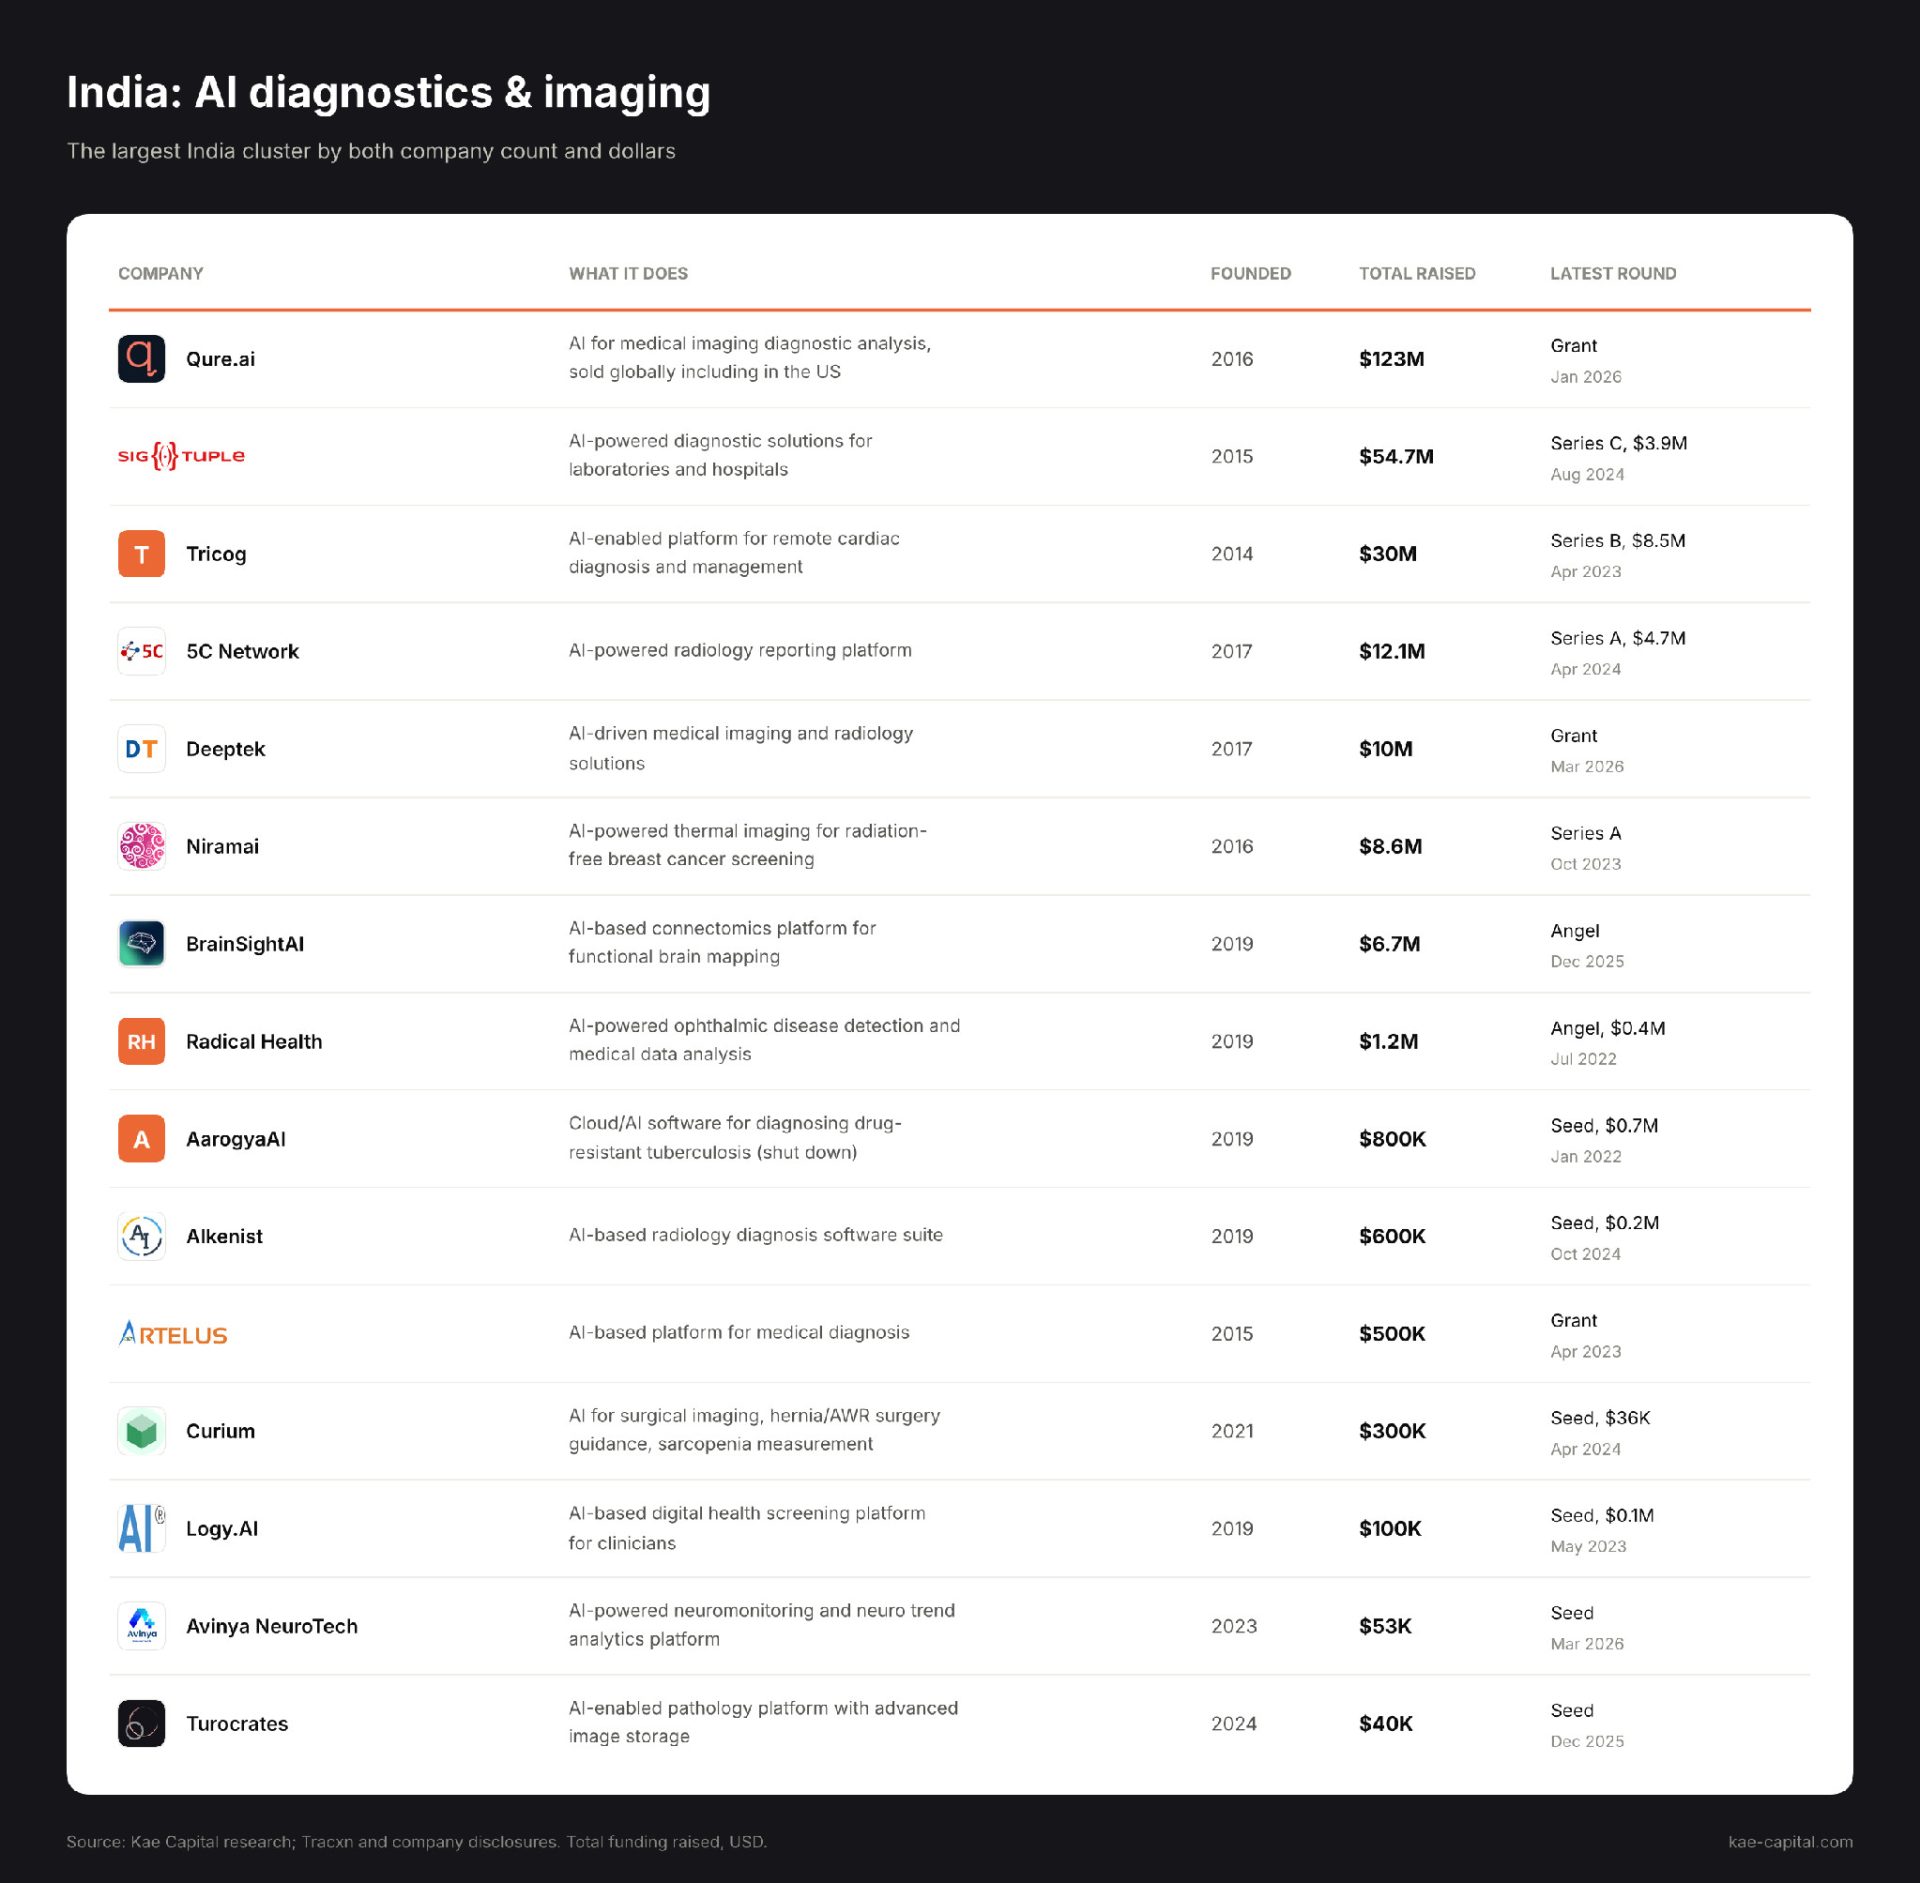
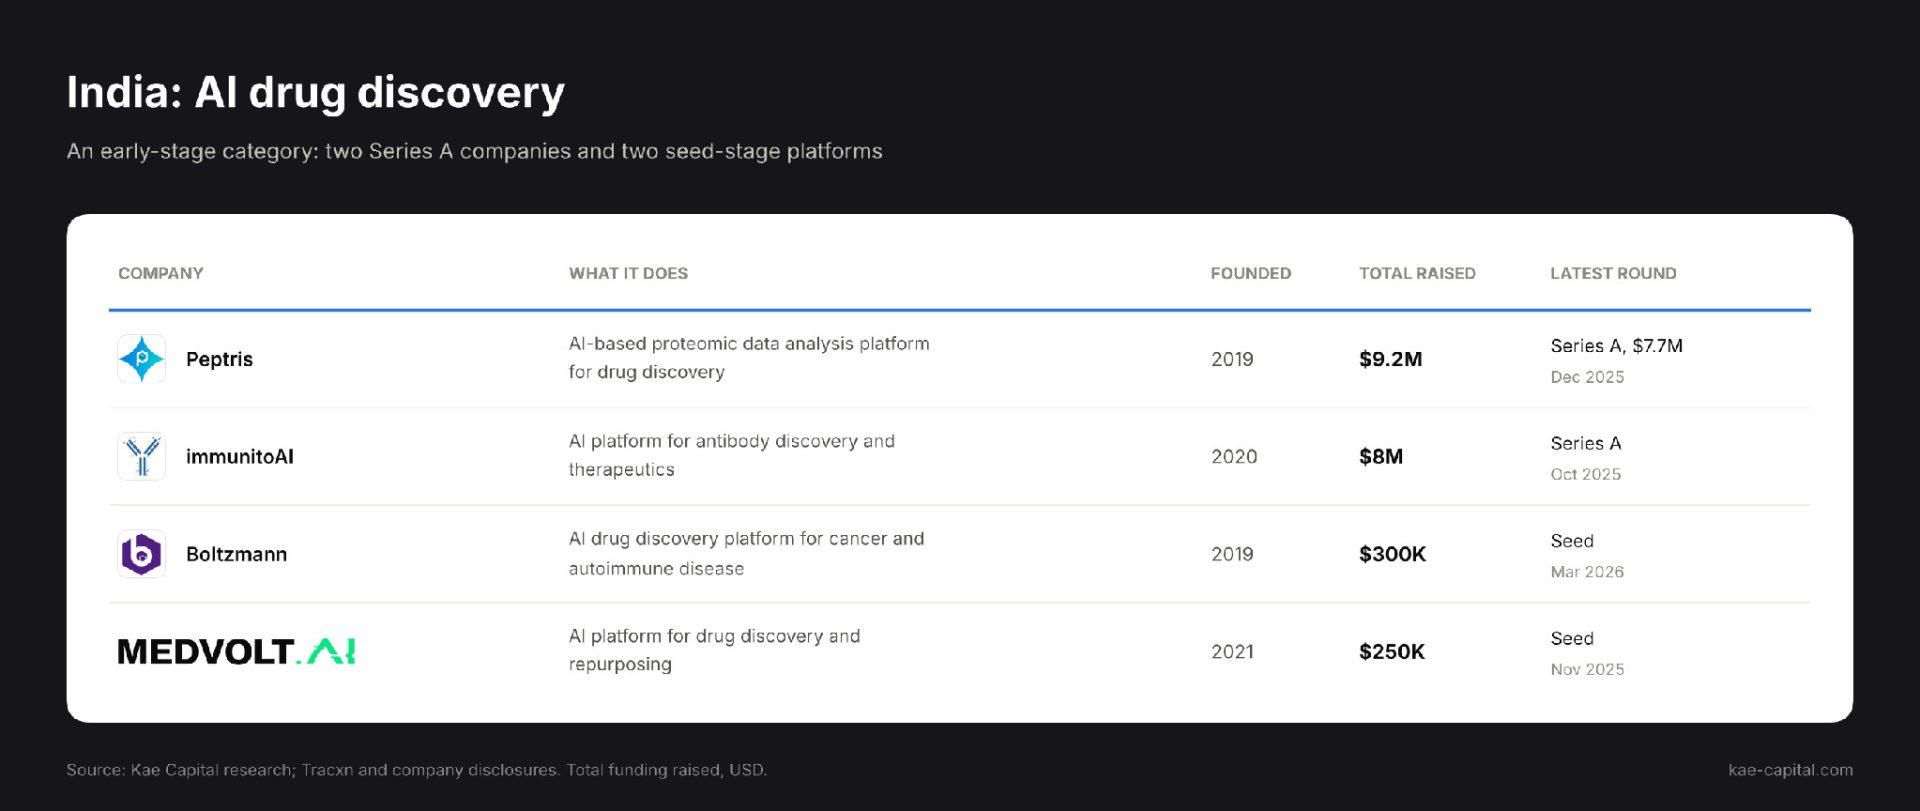
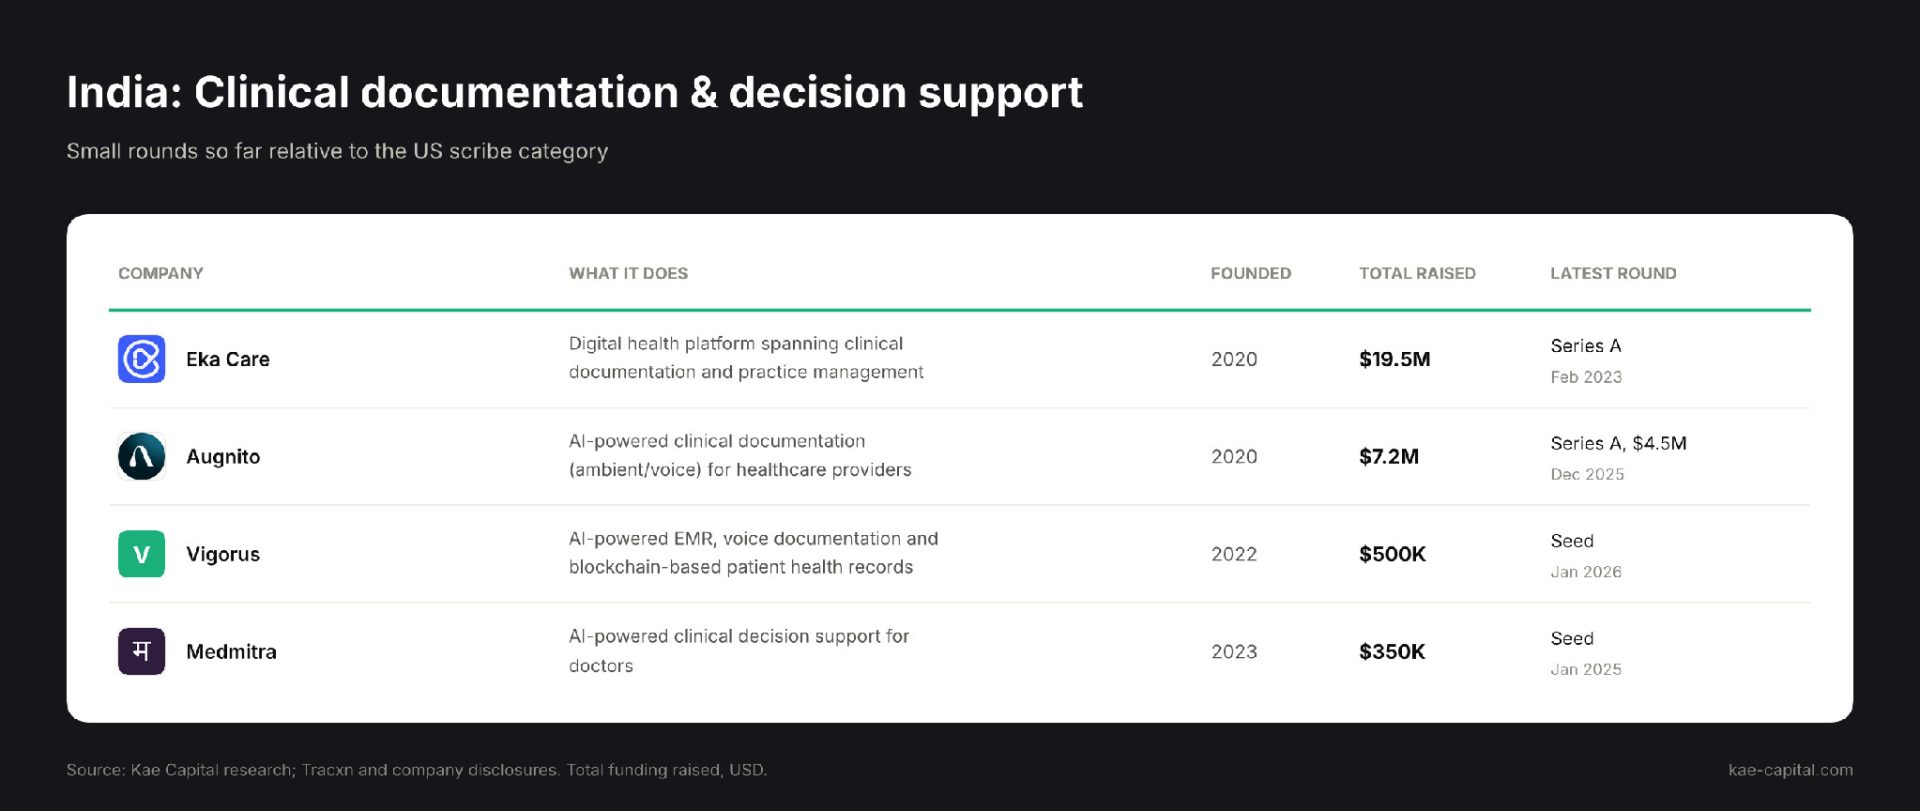
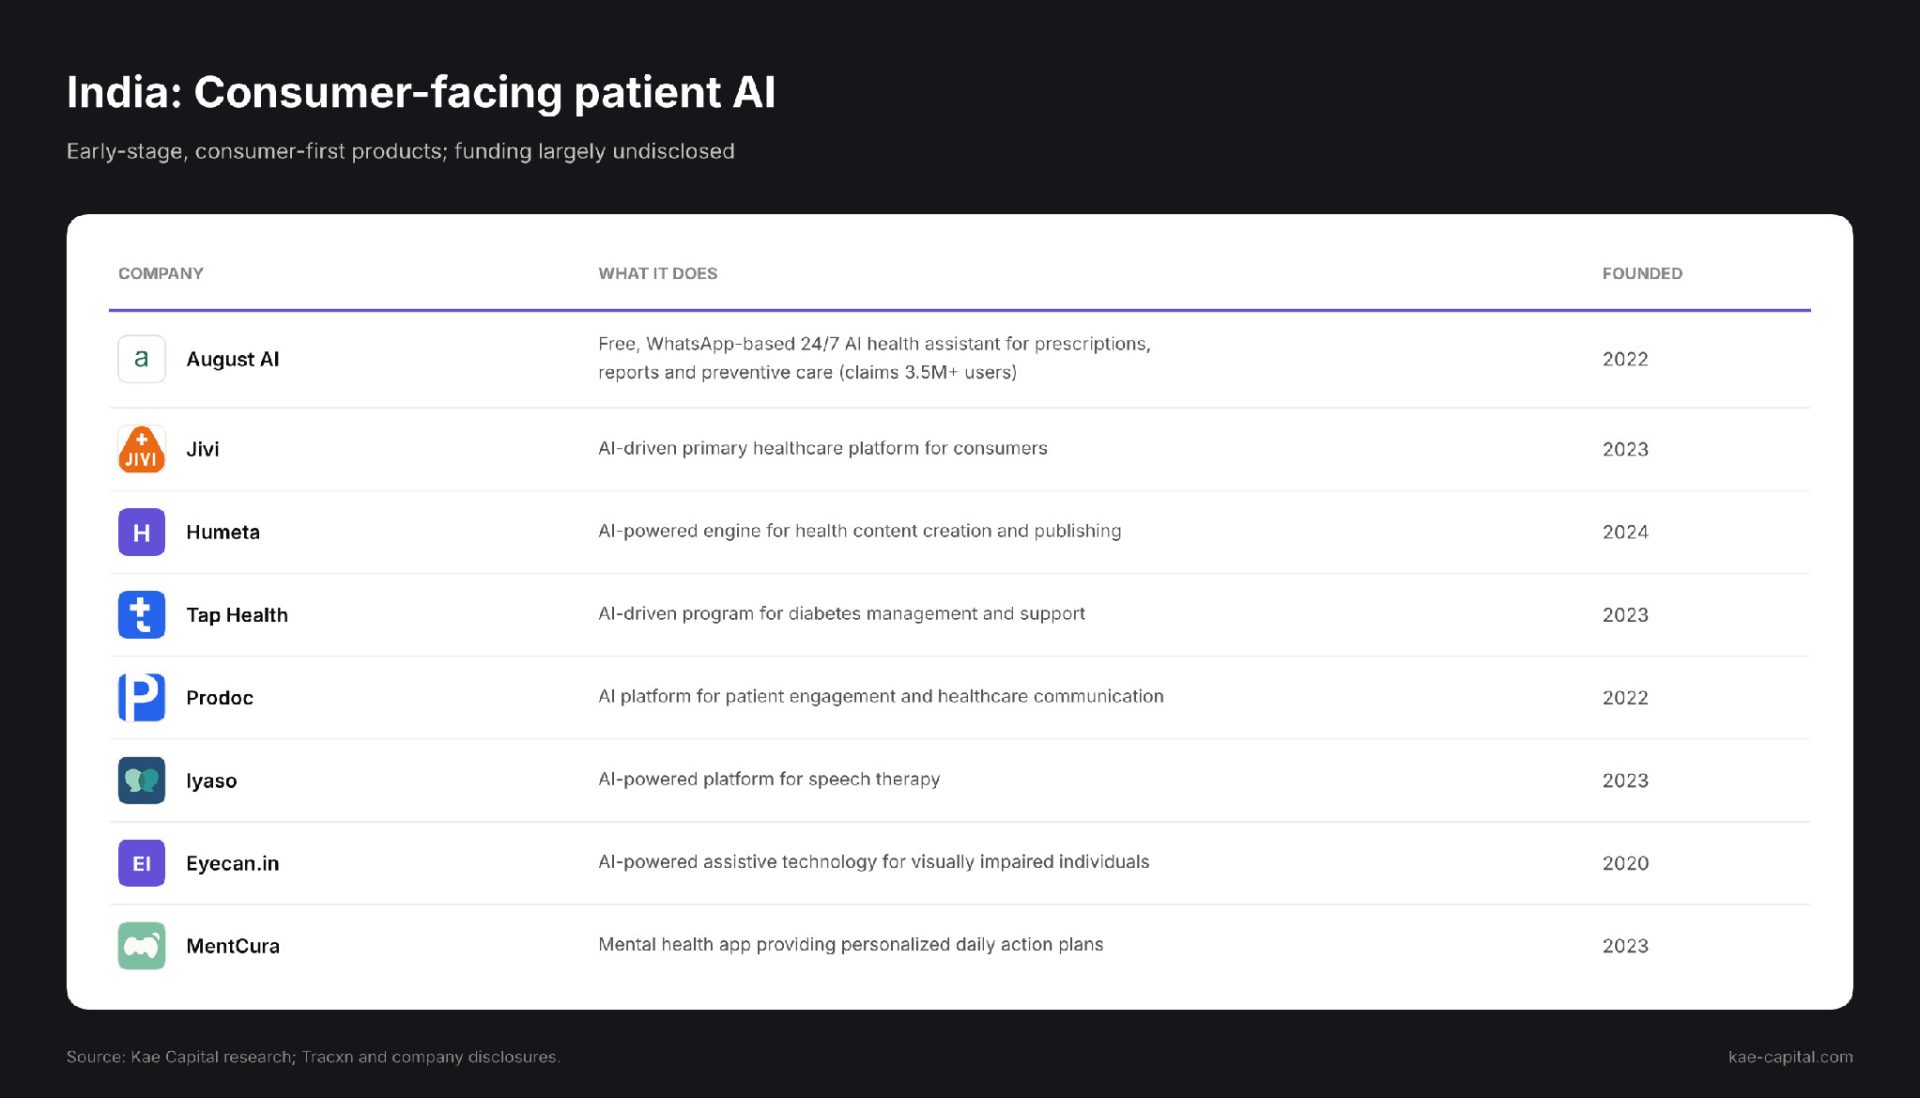
India’s healthcare AI market is still a fraction of the US one. The 36 Indian companies profiled below have raised about $380 million in disclosed funding, less than a third of what Freenome alone has raised. Diagnostics and imaging, the largest cluster, totals roughly $248 million against about $5.3 billion for the same category in the US, and Qure.ai accounts for about half of that. Most companies here are at seed or Series A.